Route of administration considerations for BORUZU®

Indication and other factors can influence clinical decisions regarding routes of administration1-3

Multiple myeloma Mantle cell lymphoma
Previously untreated disease
Image, icon of an IV bag representing IV administration. OR Image, icon of a syringe representing subcutaneous administration.
Image, icon of an IV bag representing IV administration.
Relapsed or refractory disease
Image, icon of an IV bag representing IV administration. OR Image, icon of a syringe representing subcutaneous administration.
Pre-existing or at high risk of peripheral neuropathy Image, icon of a syringe representing subcutaneous administration. Image, icon of a syringe representing subcutaneous administration.
Hepatic impairment
Image, icon of an IV bag representing IV administration. OR Image, icon of a syringe representing subcutaneous administration.
  • Image, icon of a syringe representing subcutaneous administration.
  • Subcutaneous administration
  • Image, icon of an IV bag representing IV administration.
  • IV administration

Please refer to the full Prescribing Information for direction regarding administration and dose modifications.

Image, icon of a patient experiencing neuropathy.

Subcutaneous administration is associated with lower rates of peripheral neuropathy1,2

  • Rates of peripheral neuropathy (all grades) were 38% with subcutaneous administration of bortezomib compared with 53% for IV administration (P=0.044)

According to the NCCN, subcutaneous bortezomib is the preferred method of administration for patients with multiple myeloma.3

Subcutaneous administration instructions

BORUZU® does not need to be reconstituted or diluted for subcutaneous administration1

Image, diagram icon of a syringe withdrawing a dose of BORUZU®.

Withdraw

  • Withdraw the appropriate BSA-based dose directly from the vial into a syringe.
  • The recommended starting dose for BORUZU® is 1.3 mg/m2.1
  • Subcutaneous administration requires no reconstitution or dilution.1
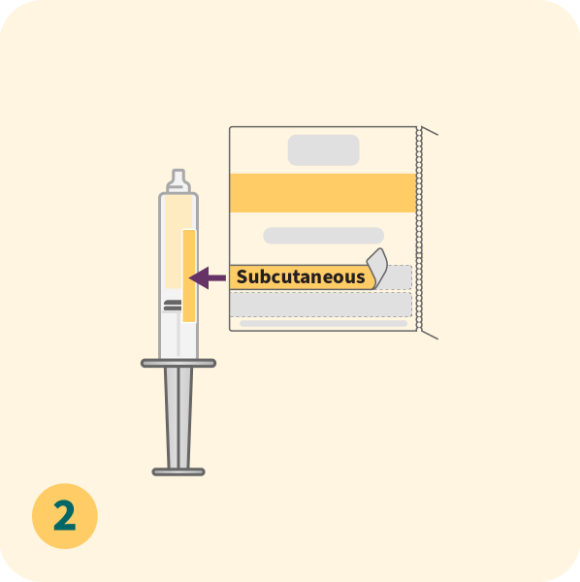
Image, diagram of a syringe labeled for the correct method of administration, "Subcutaneous".

Syringe labels

  • Place included sticker on syringe to identify the correct method of administration.1
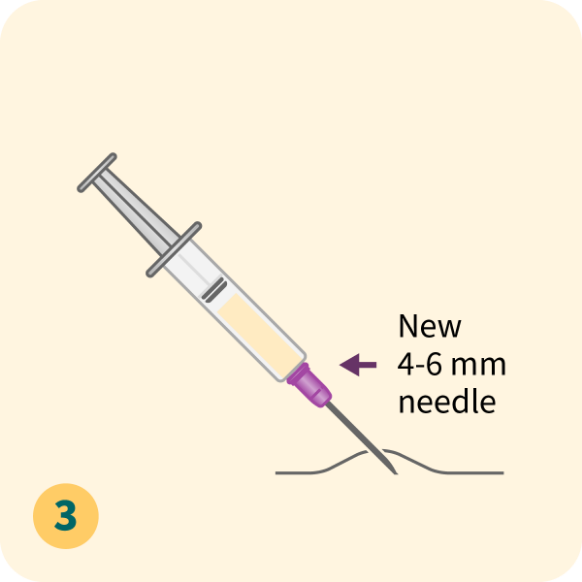
Image, diagram of a syringe affixed with a new 4-6 mm needle.

Administer

  • Attach a fresh needle (4-6 mm) to syringe with prepared medication. Administer BORUZU® to patients using institution protocol for subcutaneous administration of chemotherapeutic agents.1,4

Please refer to the full Prescribing Information for dose modification and treatment cycle recommendations.
Recommendations for subcutaneous administration

Injection site reactions may occur with subcutaneous administration of bortezomib1

When administering BORUZU® subcutaneously:

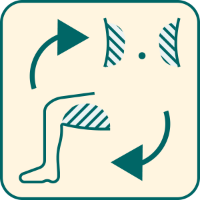
Image, diagram showing how injection sites need to rotate between the thigh and the abdomen.

Rotate the sites for each injection
(thigh or abdomen).1

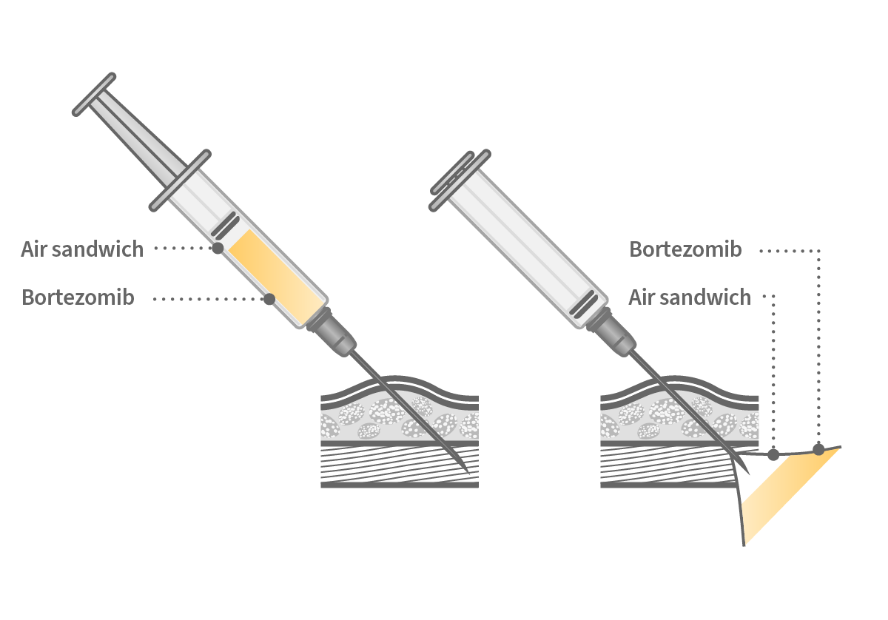
Image, icon of a syringe depicting the air sandwich injection technique.

Consider using the air sandwich (also known
as air lock) injection technique.4-6
If a local injection site reaction occurs following administration, BORUZU® may be administered at a less concentrated dose (1 mg/mL instead of 2.5 mg/mL).1

Steps for air sandwich injection technique4:

  1. Withdraw BORUZU® from the vial. DO NOT exceed the maximum volume of 2 mL per injection site.
  2. Attach a new 4-6 mm needle to syringe with prepared medication.
  3. DO NOT purge the needle of air.
  4. Pull 0.5-1.0 mL of air into the syringe (air behind drug when inverted).
  5. Invert syringe and inject contents at a 90° angle for needles 4-6 mm, or at a 45° angle for needles ≥8 mm, including the air behind the drug.
Image, diagram showing the air sandwich injection technique.

IV administration instructions1

BORUZU® must be diluted prior to IV administration

Image, diagram demonstrating an IV bag being diluted with 0.9% sodium chloride injection.

Dilute

  • Dilute each vial with 2.1 mL of 0.9% sodium chloride injection only to obtain a final concentration of 1 mg/mL.
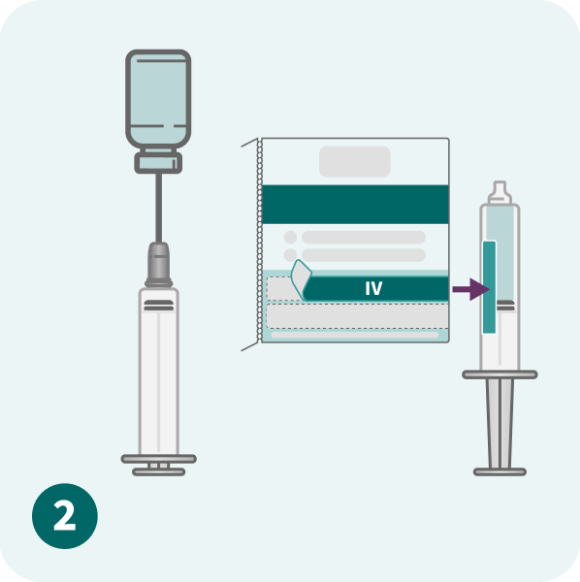
Image, diagram demonstrating the withdrawal of the appropriate BSA-based dose into a syringe that is labeled as "IV", which is the correct method of administration.

Withdraw

  • Withdraw the appropriate BSA-based dose into a syringe.
  • The recommended starting dose for BORUZU® is 1.3 mg/m2.
  • Place included sticker on syringe to identify the correct method of administration.
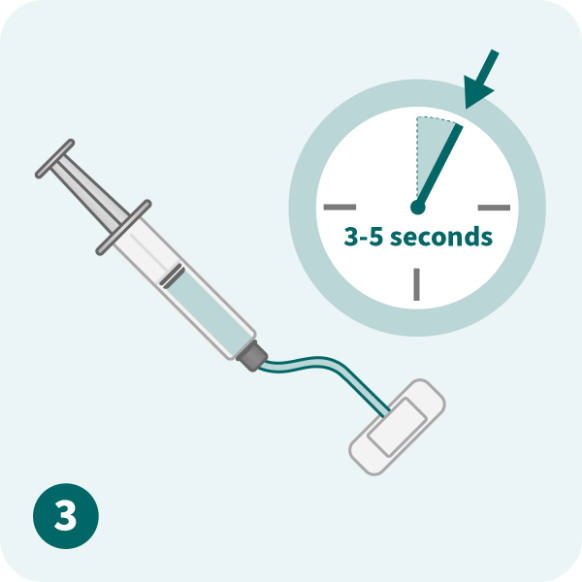
Image, diagram showing how BORUZU® is administered as a 3- to 5-second bolus IV injection.

Administer

  • Administer BORUZU® as a 3- to 5-second bolus IV injection.

Please refer to the full Prescribing Information for dose modification and treatment cycle recommendations.

Use caution when calculating the volume to be administered.

Once diluted, BORUZU® may be stored in the original vial and/or syringe at room temperature (20°C to 25°C [68°F to 77°F]) for up to 8 hours prior to use when exposed to normal indoor lighting.1


NCCN makes no warranties of any kind whatsoever regarding their content, use or application and disclaims any responsibility for their application or use in any way.

*While it is possible to administer BORUZU® intravenously for patients who have or are at risk for peripheral neuropathy, subcutaneous administration is preferred.1,3

BSA, body surface area; IV, intravenous.

References: 1. BORUZU. Prescribing information. Amneal Pharmaceuticals LLC; 2025. 2. Arnulf B, Pylypenko H, Grosicki S, et al. Updated survival analysis of a randomized phase III study of subcutaneous versus intravenous bortezomib in patients with relapsed multiple myeloma. Haematologica. 2012;97(12):1925-1928. 3. Referenced with permission from the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for Multiple Myeloma V.5.2026. © National Comprehensive Cancer Network, Inc. 2026. All rights reserved. Accessed June 25, 2026. To view the most recent and complete version of the guideline, go online to NCCN.org. 4. Kurtin S, Knop CS, Milliron T. Subcutaneous administration of bortezomib: strategies to reduce injection site reactions. J Adv Pract Oncol. 2012;3(6):406-410. 5. Boudreau A. Practical considerations for the integration of subcutaneous targeted therapies into the oncology clinic. Can Oncol Nurs J. 2019;29(4):267-270. 6. Becze E. Make subcutaneous administration more comfortable for your patients. January 4, 2022. Accessed January 6, 2024. https://www.ons.org/publications-research/voice/news-views/01-2022/make-subcutaneous-administration-more-comfortable

BORUZU® storage and ordering

BORUZU® (bortezomib injection) Important Safety Information

BORUZU® is a proteasome inhibitor indicated for:

  • Treatment of adult patients with multiple myeloma
  • Treatment of adult patients with mantle cell lymphoma

DOSAGE AND ADMINISTRATION:

BORUZU® is for subcutaneous or intravenous use only. Because each route of administration has a different final concentration, caution should be used when calculating the volume to be administered.

CONTRAINDICATIONS

  • BORUZU® is contraindicated in patients with hypersensitivity (not including local reactions) to bortezomib, boron, or mannitol. Reactions have included anaphylactic reactions.
  • BORUZU® is contraindicated for intrathecal administration. Fatal events have occurred with intrathecal administration of BORUZU®.

WARNINGS AND PRECAUTIONS

Peripheral Neuropathy: Bortezomib treatment causes a peripheral neuropathy that is predominantly sensory; however, cases of severe sensory and motor peripheral neuropathy have been reported. Patients with pre-existing symptoms (numbness, pain or a burning feeling in the feet or hands) and/or signs of peripheral neuropathy may experience worsening peripheral neuropathy (including ≥ Grade 3) during treatment with bortezomib. Patients should be monitored for symptoms of neuropathy, such as a burning sensation, hyperesthesia, hypoesthesia, paresthesia, discomfort, neuropathic pain or weakness. Starting bortezomib subcutaneously may be considered for patients with pre-existing or at high risk of peripheral neuropathy.

Patients experiencing new or worsening peripheral neuropathy during bortezomib therapy may require a decrease in the dose and/or a less dose-intense schedule. The long-term outcome of peripheral neuropathy has not been studied in mantle cell lymphoma.

Hypotension: Treatment with BORUZU® may cause hypotension. Patients with a history of syncope, patients receiving medications known to be associated with hypotension, and patients who are dehydrated may be at increased risk of hypotension. Management of orthostatic/postural hypotension may include adjustment of antihypertensive medications, hydration, and administration of mineralocorticoids and/or sympathomimetics.

Cardiac Toxicity: Acute development or exacerbation of congestive heart failure and new onset of decreased left ventricular ejection fraction have occurred during bortezomib therapy, including reports in patients with no risk factors. Patients with risk factors for, or existing heart disease should be frequently monitored. There have also been isolated cases of QT-interval prolongation in clinical studies, although causality has not been established.

Pulmonary Toxicity: Acute Respiratory Distress Syndrome (ARDS) and acute diffuse infiltrative pulmonary disease of unknown etiology such as pneumonitis, interstitial pneumonia, and lung infiltration have occurred in patients receiving BORUZU®. Some of these events have been fatal. In the event of new or worsening cardiopulmonary symptoms, consider interrupting bortezomib until a prompt and comprehensive diagnostic evaluation is conducted.

Posterior Reversible Encephalopathy Syndrome (PRES): PRES has occurred in patients receiving BORUZU® which can present with seizure, hypertension, headache, lethargy, confusion, blindness, and other visual and neurological disturbances. Brain imaging, preferably MRI (Magnetic Resonance Imaging), is used to confirm the diagnosis. In patients developing PRES, discontinue BORUZU®. The safety of reinitiating BORUZU® therapy in patients previously experiencing PRES is not known.

Gastrointestinal Toxicity: BORUZU® treatment can cause nausea, diarrhea, constipation, and vomiting, which may require the use of antiemetic and antidiarrheal medications. Ileus has also been reported. Fluid and electrolyte replacement should be administered to prevent dehydration, and BORUZU® should be interrupted for severe symptoms.

Thrombocytopenia/Neutropenia: Bortezomib is associated with thrombocytopenia and neutropenia that follow a cyclical pattern with nadirs occurring following the last dose of each cycle and typically recovering prior to initiation of the subsequent cycle. Monitor complete blood counts (CBC) frequently during treatment and assess platelet counts prior to each dose of BORUZU®. If thrombocytopenia develops, adjust the dose/schedule as outlined in the full prescribing information. Gastrointestinal and intracerebral hemorrhage have been reported in association with thrombocytopenia during BORUZU® treatment. Manage patients with transfusions and supportive care according to published guidelines.

Tumor Lysis Syndrome: Tumor lysis syndrome has been reported with BORUZU® therapy. Patients at risk of tumor lysis syndrome are those with high tumor burden prior to treatment. Monitor patients closely and take appropriate precautions.

Hepatic Toxicity: Cases of acute liver failure have been reported in patients receiving multiple concomitant medications and in those with serious underlying medical conditions. Other reported hepatic reactions include hepatitis, increases in liver enzymes, and hyperbilirubinemia. Interrupt BORUZU® therapy to assess reversibility. There is limited rechallenge information in these patients.

Thrombotic Microangiopathy: Cases, sometimes fatal, of thrombotic microangiopathy, including thrombotic thrombocytopenic purpura/hemolytic uremic syndrome (TTP/HUS), have been reported in the postmarketing setting in patients who received bortezomib. Monitor for signs and symptoms of TTP/HUS and if the diagnosis is suspected, stop bortezomib and evaluate. If the diagnosis of TTP/HUS is excluded, consider restarting bortezomib. The safety of reinitiating bortezomib therapy in patients previously experiencing TTP/HUS is not known.

Embryo-Fetal Toxicity: Bortezomib can cause fetal harm when administered to a pregnant woman. Advise females of reproductive potential to use effective contraception during treatment with BORUZU® and for seven months following treatment. Advise males with female partners of reproductive potential to use effective contraception during treatment with BORUZU® and for four months following treatment. If BORUZU® is used during pregnancy or if the patient becomes pregnant during BORUZU® treatment, the patient should be apprised of the potential risk to the fetus.

ADVERSE REACTIONS

  • The most common adverse reactions in adults (≥ 20%) for treatment of multiple myeloma include thrombocytopenia, neutropenia, anemia, leukopenia, lymphopenia, nausea, diarrhea, vomiting, constipation, peripheral neuropathy, neuralgia, anorexia, pyrexia, and fatigue.
  • The most common adverse reactions in adults (≥ 20%) for treatment of mantle cell lymphoma include neutropenia, leukopenia, anemia, thrombocytopenia, lymphopenia, peripheral neuropathy, pyrexia, nausea, and diarrhea.
  • These are not all the possible side effects of BORUZU®. Please see the full Prescribing Information for additional safety information and talk to your doctor for medical advice about side effects.

DRUG INTERACTIONS:

  • Strong CYP3A4 Inducers: Coadministration with a strong CYP3A4 inducer decreases the exposure of bortezomib which may decrease bortezomib efficacy. Avoid coadministration with strong CYP3A4 inducers.
  • Strong CYP3A4 Inhibitors: Coadministration with a strong CYP3A4 inhibitor increases the exposure of bortezomib which may increase the risk of bortezomib toxicities. Monitor patients for signs of bortezomib toxicity and consider a bortezomib dose reduction if bortezomib must be given in combination with strong CYP3A4 inhibitors.

USE IN SPECIFIC POPULATIONS

  • Pregnancy: Bortezomib can cause fetal harm when administered to a pregnant woman. There are no studies with the use of bortezomib in pregnant women to inform drug-associated risks. Advise pregnant women of the potential risk to the fetus.
  • Lactation: There are no data on the presence of bortezomib or its metabolites in human milk, the effects of the drug on the breastfed child, or the effects of the drug on milk production. Because many drugs are excreted in human milk and because the potential for serious adverse reactions in a breastfed child from bortezomib is unknown, advise nursing women not to breastfeed during treatment with bortezomib and for two months after treatment.
  • Females and Males of Reproductive Potential: Bortezomib can cause fetal harm when administered to a pregnant woman. Conduct pregnancy testing in females of reproductive potential prior to initiating bortezomib treatment. Females of reproductive potential should be advised to use effective contraception during treatment with bortezomib and for seven months after the last dose. Males with female partners of reproductive potential should be advised to use effective contraception during treatment with bortezomib and for four months after the last dose. Based on the mechanism of action and findings in animals, bortezomib may have an effect on either male or female fertility
  • Pediatric Use: Safety and effectiveness of bortezomib have not been established in pediatric patients.
  • Geriatric Use: No overall differences in safety or effectiveness were observed between patients ≥ age 65 and younger patients receiving bortezomib; but greater sensitivity of some older individuals cannot be ruled out.
  • Renal Impairment: No starting dosage adjustment of bortezomib is recommended for patients with renal impairment. In patients requiring dialysis, bortezomib should be administered after the dialysis procedure.
  • Hepatic Impairment: No starting dosage adjustment of bortezomib is recommended for patients with mild hepatic impairment (total bilirubin ≤ 1 × ULN and AST > ULN, or total bilirubin > 1 to 1.5 × ULN and any AST). The exposure of bortezomib is increased in patients with moderate (total bilirubin ≥ 1.5 to 3 × ULN and any AST) and severe (total bilirubin > 3 × ULN and any AST) hepatic impairment. Reduce the starting dose in patients with moderate or severe hepatic impairment
  • Patients with Diabetes: During clinical trials, hypoglycemia and hyperglycemia were reported in diabetic patients receiving oral hypoglycemics. Patients on oral antidiabetic agents receiving bortezomib treatment may require close monitoring of their blood glucose levels and adjustment of the dose of their antidiabetic medication.

To report SUSPECTED ADVERSE REACTIONS, contact Amneal Global Patient Safety at 1-877-835-5472, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

Please read the full Prescribing Information.

BORUZU® (bortezomib injection) Important Safety Information

BORUZU® is a proteasome inhibitor indicated for:

  • Treatment of adult patients with multiple myeloma
  • Treatment of adult patients with mantle cell lymphoma